The tendon is continuous
A healthy supraspinatus crosses over the top of the humeral head and attaches firmly to the bone.
Why it matters: A continuous tendon helps compress and center the ball during motion.

The rotator cuff is four small tendons that keep the ball of your shoulder centered and help you lift and turn your arm. Tears are very common, especially after 50. Some need surgery, many do not. This page explains how to tell the difference, using the best current research.
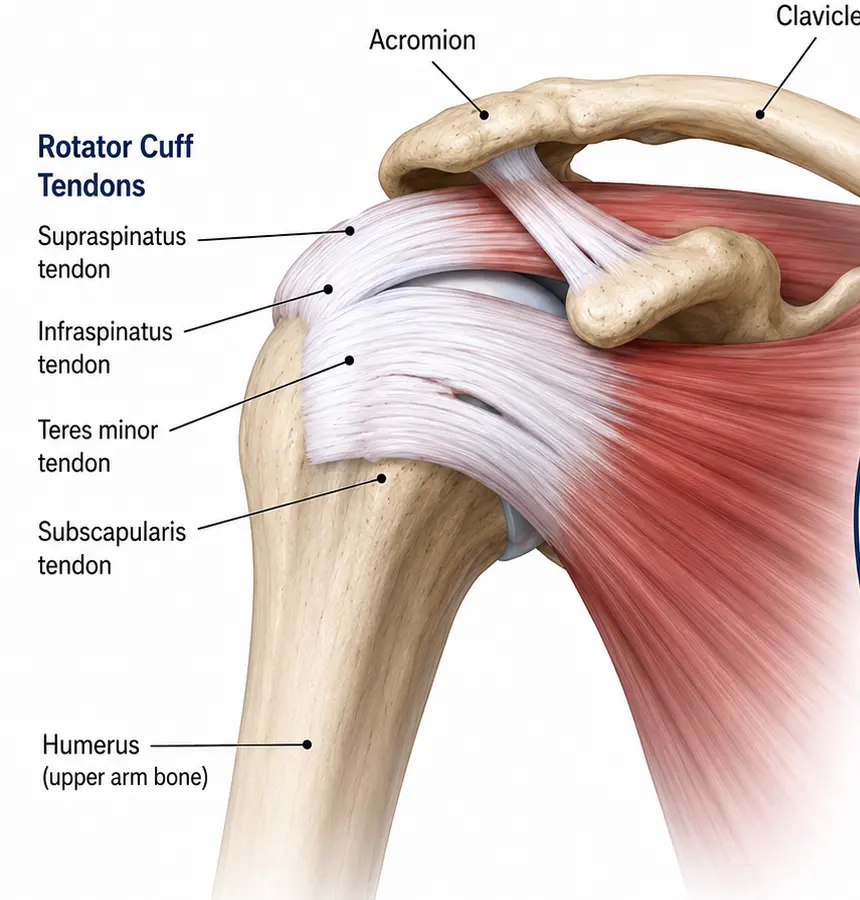
Your shoulder is a ball sitting on a shallow socket, like a golf ball on a tee. The rotator cuff wraps around the ball like a hand holding it in place. While the big deltoid muscle lifts the arm, the cuff keeps the ball centered so the motion is smooth and strong. Tap a tendon to see what it does.
Drag the slider to see how the tendon changes from healthy and fully attached to partial, full-thickness, and retracted tears.
There are two main paths. Many tears are a mix of both: an older, quiet tear that gets bigger with a fall or a lift.
You suddenly cannot lift your arm after a fall or injury. Acute traumatic tears do best when they are evaluated within a few weeks, because the tendon can pull back and the muscle can weaken over time.
X-rays show bone, arthritis and spurs. Ultrasound and MRI show the tendons. An MRI is very good at finding tears, but finding a tear is not the same as finding the cause of your pain. Tears become common with age, even in shoulders that feel fine.
411 volunteers without shoulder symptoms. Tempelhof et al., J Shoulder Elbow Surg 1999.
That is why Dr. Ramirez matches the scan to your history and exam. Stiffness (frozen shoulder), arthritis, biceps problems and pinched nerves in the neck can all cause similar pain.
Not always, but often enough that we watch full-thickness tears instead of forgetting about them. Research that followed people with untreated tears for several years found:
Tears in the dominant arm were more likely to grow and become painful. New weakness, or pain that changes character, is a reason to recheck the tendon.
Pick the description closest to you to see the usual starting point and the research behind it. This is a guide for your visit, not a diagnosis.
Therapy does not reattach a torn tendon. What it does is strengthen the healthy parts of the cuff and the shoulder-blade muscles so they take over the work, and that is enough for many people to become pain-free.
Avoid the motions that hurt most, without putting the arm in a sling. Short courses of acetaminophen or an anti-inflammatory if safe for you. Ice or heat for comfort.
Restore motion, then strengthen the cuff, deltoid and shoulder-blade muscles. A well-taught home program works as well as frequent supervised visits for many patients.
A single injection with numbing medicine can ease pain for weeks to a few months so therapy can work. We avoid repeated injections because they may weaken the tendon and affect healing if you later need surgery.
If you are better, keep up the exercises. If pain or weakness persists, or the tear is the type that does better with repair, we talk about surgery.
Platelet-rich plasma (PRP) and "stem cell" injections are widely advertised. The evidence for them in rotator cuff tears is still limited and mixed, and they are not a substitute for repair when a tendon is torn off the bone.
Most repairs are done arthroscopically through several small incisions as an outpatient. Small anchors placed in the bone hold sutures that pull the tendon back to where it belongs, so it can heal to the bone. Healing takes about 12 weeks, which is why the sling and the early rules matter.
| Procedure | What it does | Typically used for |
|---|---|---|
| Arthroscopic rotator cuff repair | Reattaches the tendon to bone with anchors and sutures. | Repairable partial and full-thickness tears. |
| Repair with graft augmentation | Adds a patch over or across the repair to support healing. The 2025 AAOS guideline supports augmentation in selected repairs. | Larger tears, poorer tissue, or revision surgery. |
| Partial repair | Fixes as much of the tendon as possible to restore balance, even if the whole tear cannot close. | Massive tears that will not fully reach the bone. |
| Subacromial balloon spacer | A dissolving balloon placed above the ball to help it glide and center. | Irreparable tears with a healthy front tendon, in less demanding patients. |
| Superior capsule reconstruction or tendon transfer | Rebuilds the top of the joint with a graft, or reroutes a nearby muscle to replace the torn one. | Younger, active patients with irreparable tears and no arthritis. |
| Reverse shoulder replacement | Replaces the joint with a design that lets the deltoid lift the arm without the cuff. | Irreparable tears with arthritis or inability to lift the arm, usually in older patients. |
In high-quality studies, roughly 1 in 6 to 1 in 5 repairs (about 15% to 21%) shows a re-tear on imaging. The risk is higher with larger and older tears, more muscle wasting, older age and smoking. Many people with a small re-tear still have much less pain than before surgery.
Removing a bone spur (acromioplasty) on its own does not improve results for most people, and is added only when the bone shape is a problem.
The repair is held by sutures while the tendon grows back into the bone. That biology sets the pace, no matter how good the shoulder feels.
Sling time is usually 4 to 6 weeks depending on tear size. Driving usually resumes at 2 to 4 weeks once you are off narcotics and out of the sling for driving. Desk work often returns within 1 to 2 weeks. Starting motion a little earlier or later gives similar long-term results for small-to-medium tears, so Dr. Ramirez adjusts timing to your tear.
A full-thickness tear does not grow back to the bone on its own. Many people still become comfortable and functional with therapy, because the rest of the cuff and shoulder muscles compensate. Some partial tears do settle down.
Age alone is not the deciding factor. Healing is somewhat less reliable with age, but the more important questions are tendon and muscle quality, your health and your goals. Healthy patients in their 70s often do well.
For small, gradual tears in older adults, waiting with therapy is reasonable and safe for most people. For sudden tears with weakness, or in younger and active patients, waiting can let the tendon pull back and the muscle weaken, which can make a later repair harder or impossible.
The first 1 to 2 weeks are the hardest. A nerve block numbs the arm for 12 to 24 hours after surgery. Scheduled acetaminophen, an anti-inflammatory when allowed, ice and a short course of narcotic for breakthrough pain keep most patients comfortable. Sleeping propped up or in a recliner helps.
Most patients regain good strength and function. Recovery continues for up to a year. Large, old tears may not return to full strength, but pain relief is usually substantial.
Yes, about 15 to 20 percent of repairs show some re-tearing on imaging, more often in large tears. Many of these patients still feel much better than before surgery. Following the sling and lifting rules lowers the risk.
Bring your MRI or ultrasound report if you have one. A focused exam tells us whether the tear is the true source of your pain and which path fits your goals.
(309) 676-5546
Great Plains Orthopaedics · Peoria, Illinois · Se habla español
This page provides general education and does not replace an examination or individualized medical advice. Last reviewed October 2026. For emergencies, call 911.